
Depression is treatable — including the kind that has not responded yet.
Some people feel better on the first medication they try. Many do not. Both situations deserve the same thing: a careful look at what is actually going on, and a plan that changes when the evidence says it should.

Depression is not only sadness
It often shows up first as something that looks like a personality change, a work problem, or a physical complaint. These are among the most common features clinicians look for — a diagnosis, though, only comes from a full evaluation.
Loss of interest
Things that used to matter — work, people, hobbies — stop registering. Often the first thing partners notice.
Sleep that changed
Waking at 3am and not getting back down, or sleeping far more than usual and still feeling flattened.
No fuel
Fatigue that rest does not fix, and a sense that ordinary tasks now take an unreasonable amount of effort.
Thinking got harder
Concentration, memory and decisions become effortful. People often assume this is burnout or aging.
Appetite shifted
Eating noticeably more or less than usual, sometimes with weight change you did not intend.
Weight of self-blame
Persistent guilt or a harsh, constant self-criticism that would not be applied to anyone else.
Three moving parts, reviewed together
Accurate diagnosis
Depression overlaps with bipolar spectrum illness, anxiety, ADHD, grief, thyroid problems and sleep disorders. Treating the wrong one is a common reason treatment stalls.
The right treatment, given a fair trial
Medication, supportive and therapeutic interventions, or a combination — at an adequate dose, for long enough to actually judge the result.
A plan for if it does not work
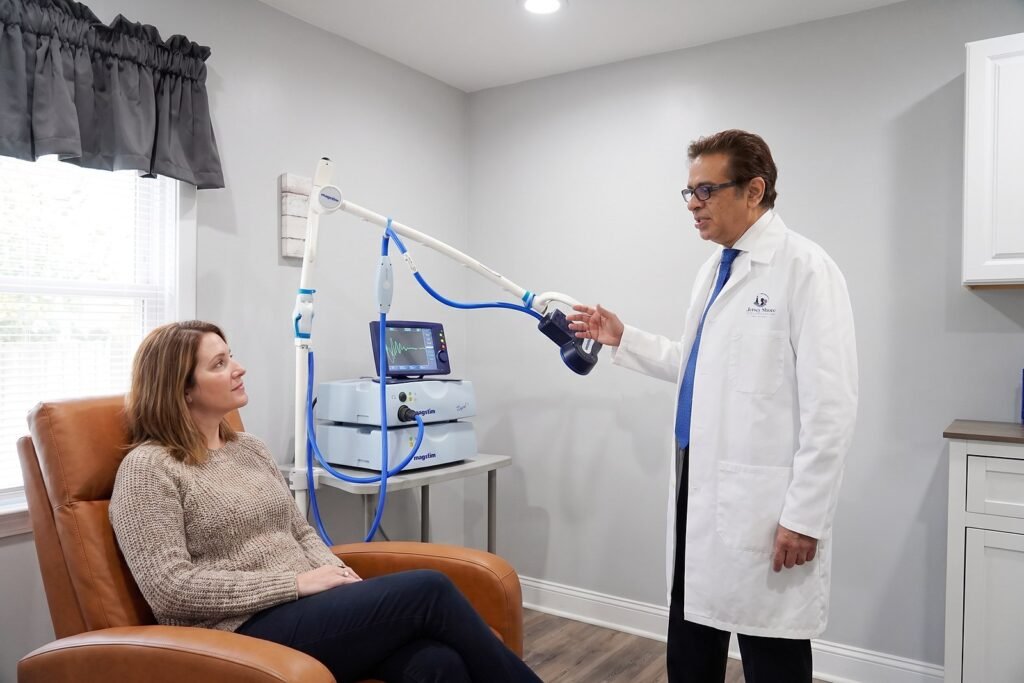
Including reassessment and evaluation for advanced options such as TMS. Not responding to the first thing is common — it is not the end of the list.
When previous treatment has not worked
Dr. Abbas has directed hospital neuromodulation and treatment-resistant mood programs since 2017. If you have already tried two or more antidepressants without an adequate response, that history is useful information. It narrows what to try next rather than starting over.
Questions people ask before coming in
No. Medication is one option, and the right one for many people, but it is not the only one and it is not automatic. What is recommended depends on what the evaluation finds and on what you want.
No. Long-standing depression is common and treatable, and a long history often means there is useful information about what has and has not worked.
That is a specific clinical situation with its own approach — reassessment of the diagnosis, a review of doses and durations, and evaluation for options including TMS.
You set the pace. The evaluation needs enough history to be accurate, but nothing about it requires you to relive more than you want to in one sitting.
If you are thinking about harming yourself, please do not wait for an appointment. Call or text 988 to reach the Suicide & Crisis Lifeline, or call 911. If you are safe and looking for ongoing care, we would be glad to see you.
You may also want to explore
Treatment-Resistant Depression
A careful reassessment when two or more treatments have not produced relief.
Medication Management
Ongoing adjustment and monitoring rather than a one-time prescription.
You do not have to have it figured out first.
Bring what you know. The evaluation is designed to work out the rest.